

There are days when I go to work as a neuropsychologist, and I get to sit across from my patient in a well-lit, comfortably furnished office with a nice wrap around desk. The work is still hard, but having a space that is tailor made for assessment makes a huge difference. And there are other days when my office looks like this:

This is a generated image, but it is quite close to what the actual environment looked like for a recent assessment that I completed. In addition to evaluating people that are sent by their doctors to determine if they may be showing signs of a dementia condition, I also go out into the field to conduct assessments in the homes of individuals that are struggling. This work is done in partnership with my county’s Adult Protective Services. They have an amazing program that allows us to discuss difficult cases and to provide services like nursing and neuropsychological assessment free of charge.
Today, I want to walk you through a recent assessment that I conducted so you can learn a bit more about how to think like a neuropsychologist. This is Volume 2 of The Brain Files (cue eerie music).

Since I am referencing real people and events, I’m going to change a lot of information here to maintain confidentiality. Please keep that in mind as you read through this.
Referral Question
Let’s start from the top. I was asked to come see a man (Bill) in his 60s due to several concerns. The most obvious concern was self-neglect, which was apparent in his home. There was grime, rotten food, paperwork, broken bottles, and other debris strewn throughout his entire house. While I did not go into the bathroom, I was told that it was full of soiled adult diapers. If you’ve ever been in homes like this, you know that the air feels thick and sharp all at once. It can be difficult to breathe and maintain composure. These situations can be tough because you want to treat the human before you with dignity, but you also have your senses of smell, sight, and taste to consider. So, you mask up, grab gloves if you have to, and do your best.
The other concern was related to mismanagement of finances including an unpaid home mortgage, unpaid HOA fees (I care less about those), and reports of no money to for adequate nutrition or personal care.
History
During my interview with Bill, he told me that he was functioning well, living in another state prior to his father falling ill, which prompted him to move across the country to stay with him and help out. Bill’s father was on hospice care, and he said that he was his father’s sole caregiver during the two years prior to his passing. Bill’s father died about a year ago.
Another major difference between typical medical referrals and these types of cases is that I often do not have the same access to medical records and alternative sources of information. So, what I was able to glean from Bill is that he had two strokes at some point, but he did not know when they were. However, he did know that he suffered a serious decline in his functioning after the occurred.
Initial Hypotheses

Before you start the formal evaluation and interpret any data, it is natural to think about what could possibly be going on here. Given Bill’s circumstances, I obviously want to consider changes in his life that could be contributing. The loss of a parent can cause serious grief for some. In some cases, the loss of a parent that was previously supporting the individual or hiding their pre-existing deficits is also an issue, but Bill said he was living independently before his dad fell ill.
So, are emotional difficulties making Bill lack the motivation to pay his bills or help himself? There were also a number of empty liquor bottles on the floor. Maybe substance abuse plays a role here as well.
Bill shared that he has had strokes. These can absolutely cause both cognitive impairment and changes in behavior depending on where the damage occurred. If he is completely forgetting to do things like pay his bills and he lacks the understanding of how he should be managing his money, we may be looking at something different altogether like Alzheimer’s disease.
Let’s continue…
More Information

As I spoke to Bill, a few things became apparent that helped me better conceptualize his situation. For one, even though he had poor hygiene, which was demonstrated in his soiled skin, hair, and nails, he was wearing new-appearing clothes. He also had various Amazon boxes and clearly brand-new books near the entryway to his home.
When I asked about how his home got to the state that we found it in, he had difficulty adequately explaining. He was certainly depressed, but from what I could gather, depression has not been a lifelong issue for him. Rather, he recently just stopped caring about everything. He feels overwhelmed by any responsibilities, and he admitted that he would rather just stop existing. This did not appear to be a grief reaction, as he had no strong feelings about his father passing.
Bill had previously received help getting him home back into a sanitary state, but over time it returned to the hoarded and unsafe environment that I witnessed. While he was open to receiving help, it seemed that Bill had a lot of trouble with follow-through, whether for matters concerning his home or his medical health. Additionally, Bill had another family member that was previously helping him manage his affairs from afar (they lived in another state), but Bill said they had since cut him off due to frustrations about Bill’s poor financial choices.
Updated Hypotheses
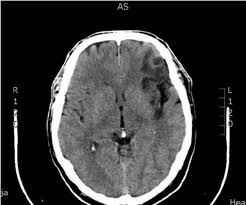
Now that I was able to get a better understanding of how Bill saw his own situation, my hypotheses were narrowed down a bit. While he certainly seemed depressed, his depression felt related to his strokes rather than grief from losing his father. Interestingly, about 30% of people that experience a stroke develop the symptom of apathy whether or not they actually have a mood disorder.
Given his poor hygiene, trouble organizing himself, lack of ability to motivate himself to take action, and significant behavioral changes, I was definitely wondering about damage to his frontal lobes at this point. Frontal involvement also jumped out at me because of his decision-making. Rather than bathe, he tended to buy new clothes. Despite having no money for fresh food, he would buy books on Amazon. These impulse control and decision-making issues are hallmarks of frontal lobe damage. If that were the case, I would expect to see some difficulties with executive functioning (higher-level thinking skills) on our evaluation.
Testing

As I mentioned, the home environment was not very friendly to the senses, and we had no place to really conduct a thorough evaluation. Luckily, I spotted a less cluttered area in Bill’s backyard, and he was open to us going out there. When you are in this line of work, you learn to pack some extra supplies, so I went out to my car to grab some folding chairs, and Bill had a little round table (albeit a little wobbly) that we could use for the assessment.
We always begin assessments with the basics. How is the person’s vision? Are they in pain? Do they speak English fluently? All of that stuff. Unfortunately, in Bill’s case, his visual acuity was horrendous despite having glasses. This limited the kinds of assessments that we were able to do. We had to mostly focus on verbal tasks and tasks that had large stimuli that he could make out.
I should also mention at this point that Bill was never some failure-to-launch man that always relied on others. He had a master’s degree and worked as an educator before taking care of his father. We would expect that Bill would have had pretty good cognitive abilities in the past. It’s with that knowledge that we begin interpreting his current performance.
Results
As a reminder, the tests that I administer are based on normative data for the individual’s demographics. That means their age and education level are factored in. If someone is only showing normal signs of aging, that’s great! We are looking for the areas that they may be deviating from the typical issues that arrive in the normal aging process. Unfortunately for Bill, there were several significant areas of impairment.
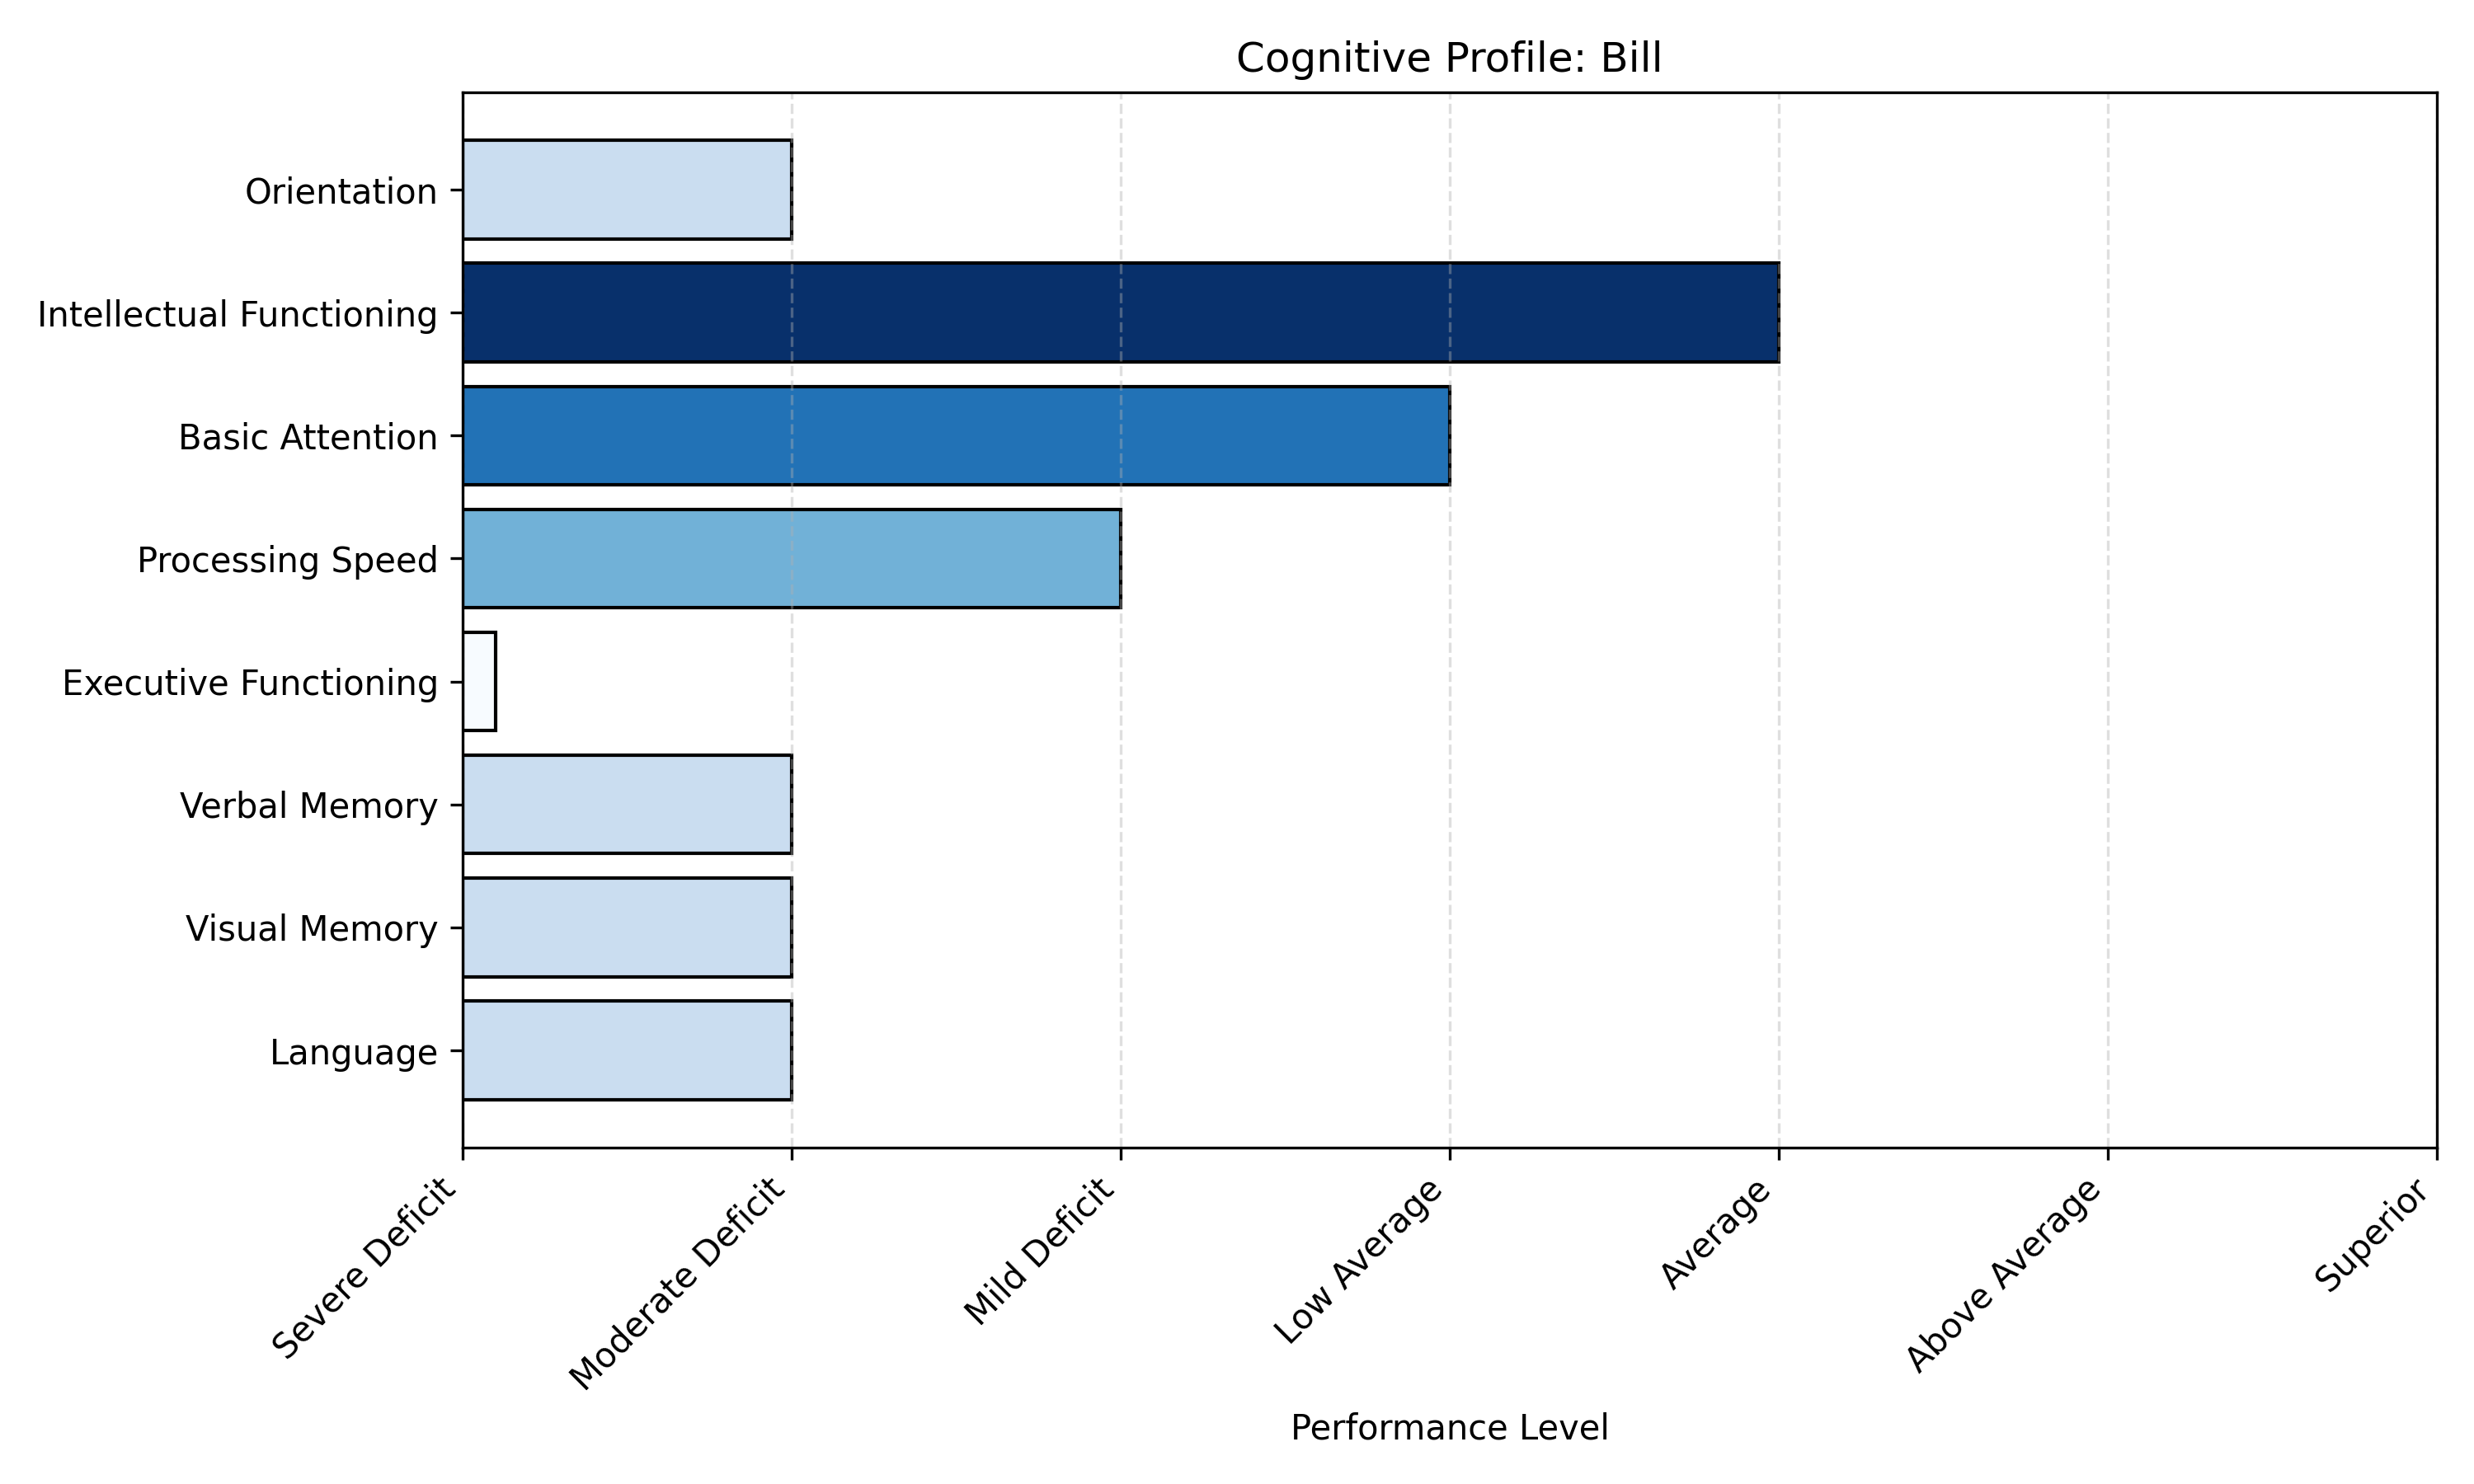
This chart shows a basic overview of Bill’s performance in each of the domains we looked at. I also did a separate evaluation to look at his understanding of financial and medical matters. For now, we will just focus on the cognitive results above.
First, let’s look at his strengths. None of the cognitive domains were stronger than expected for his age. He did fine on basic attention, which means he is able to hold onto information for a moment, but that doesn’t mean he is necessarily able to remember it later.
Above, I mentioned that for someone that seems to have issues with their frontal lobe, we would expect to see deficits in executive functioning on testing? That was absolutely the case will Bill. He demonstrated essentially no ability to multitask or organize his thoughts. He also struggled majorly on a test that should have come more easily to him. We did a couple tests of “verbal fluency” which simply required him to say as many words of a given letter or as many words from a given category out loud as he could in a minute. Within a minute, Bill was only able to produce one word per trial for letter fluency.
When translating these scores to real life, this means that Bill has an extremely hard time initiating activities, managing multiple demands, and thinking through the potential outcomes of his actions. You can probably see how this might turn into the type of hoarding situation that Bill found himself in. The tough part is that as issues pile up, it becomes even more demanding on executive functioning, which can cause someone like Bill to shut down entirely.
We don’t have to go through every aspect of his cognitive performance, but there is one other nuanced result that I’d like to point out. In the chart, you see that intellectual functioning is intact. That’s not totally true. When you look at reasoning or intellectual functioning, you are essentially talking about IQ. The number that you see for IQ is actually an average made up of several different tests and indices. For Bill, we were only able to do verbal IQ tests. He did great on a test that measured general knowledge, using trivia-style questions, but his performance was weaker than 98% of people his age on a test that required more abstract reasoning. This skill is tied to frontal lobe functioning, which helps bolster the hypothesis that something is amiss there.
Last overt difficulty that I want to draw your attention to is his memory functioning. I wasn’t necessarily expecting to see this, but Bill’s memory was abysmal. His long-term memory was fine, but when he was asked to remember a list or words, a short story, or a picture he had been shown, his performance was quite impaired across the board.
Putting it All Together

Alright, now we have the presenting issue of hoarding, non-payment and self-neglect. We have the known history of strokes. And we have his results of neuropsych testing. But what do we do with all of this for the case of Bill?
Since this is a case that I saw for APS, I look at things a little differently than a straightforward clinical case. Rather than establishing a diagnosis, my primary concern is to determine if this person has capacity to care for themselves and make decisions independently. For Bill, the answer here was a resounding “no.” Not only did he have no insight into how his situation deteriorated to this point, but he also had plan to improve things, and he failed formal measures of independent living ability.
When someone lacks capacity, I typically then go on to fill out a formal government form called a capacity declaration. From there, a family member or a local entity may step in to take conservatorship of the person and help them get into a safer situation.
However, I do try to provide some opinion on potential diagnoses or areas for follow-up, even in these more forensic contexts. The most obvious source of his impairment would be history of strokes with questionable follow up regarding after care. An MRI would probably show extensive damage in his frontal lobes.
The memory issue is curious, though. Certainly, memory impairment can also be caused by strokes. Truly, they can impact any number of cognitive abilities depending on where the stroke occurred. However, given the extent of his memory loss and some trouble with language, we would also want to rule out a progressive illness like Alzheimer’s disease. Unfortunately, there is no magical rule that says you can only have one devastating brain issue. You can absolutely have both, which we would refer to as a mixed dementia.
What Now?
My greatest hope is that this will start Bill on the path to getting some help. He needs someone to step in and stop his money from disappearing. He needs to get adequate medical care, and the source of his cognitive and behavioral issues needs to be looked into by a neurologist. If even a part of this can be treated medically, that would be awesome.
Bill also needs to be placed somewhere that he can be supported. Because of his executive dysfunction, everything feels overwhelming to him, and he has very little ability to manage his impulses.
Bill was a sweet guy, though. And he expressed that he really wanted help, but he simply had no idea what to do. This is a case where I can see him thriving in a supportive environment with someone else to manage his financial and medical care.
